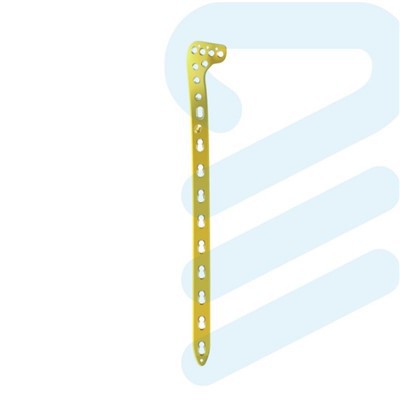
The dynamic compression plate (DCP) has been a cornerstone in orthopedic trauma surgery for decades. As a supplier of high - quality DCPs, I have witnessed the evolution of its design and application. One of the critical factors that can influence the treatment outcome of using a DCP is its length. In this blog, I will delve into how the length of a DCP affects the treatment outcome from multiple aspects.


Biomechanical Considerations
The length of a DCP plays a significant role in the biomechanics of the fracture site. When a fracture occurs, the bone loses its structural integrity, and the DCP is used to restore stability and promote healing. A shorter DCP may not provide sufficient stability across the fracture site. For example, in a long - bone fracture, if the plate is too short, the forces acting on the fracture during normal daily activities or weight - bearing can cause excessive movement at the fracture site. This excessive movement can disrupt the formation of callus, which is essential for bone healing. Studies have shown that in femoral shaft fractures, a shorter DCP may lead to higher rates of non - union due to inadequate load - sharing between the plate and the bone [1].
On the other hand, a longer DCP can distribute the stress more evenly along the bone. By spanning a greater length of the bone, it reduces the stress concentration at the fracture site. This is particularly important in fractures where the bone is subjected to high - magnitude forces, such as those in the lower extremities. The long - plate construct allows the bone to bear a portion of the load, which is beneficial for bone remodeling. However, an overly long DCP may also have drawbacks. It can lead to stress shielding, where the plate takes on too much of the load, and the bone is not stimulated enough to remodel properly. This can result in bone atrophy over time, making the bone more susceptible to future fractures [2].
Fracture Type and Location
The type and location of the fracture also interact with the DCP length to affect treatment outcomes. In comminuted fractures, a longer DCP is often preferred. Comminuted fractures involve multiple fragments, and a long plate can help hold these fragments in place and provide stability. For instance, in a comminuted tibial fracture, a long DCP can span the entire area of the fracture, reducing the risk of fragment displacement and promoting better alignment.
When it comes to the location of the fracture, different bones have different requirements. In the upper extremities, where the forces are generally lower compared to the lower extremities, a shorter DCP may be sufficient in some cases. For example, in a simple radius fracture, a relatively short DCP can provide adequate stability for the bone to heal. However, in the lower extremities, especially in weight - bearing bones like the femur and tibia, longer DCPs are more commonly used. The increased length helps to withstand the higher forces associated with walking and standing.
Soft - Tissue Considerations
The length of the DCP can also impact the soft - tissue environment around the fracture site. A longer DCP requires a larger surgical incision for implantation. This can lead to more extensive soft - tissue dissection, which increases the risk of surgical complications such as infection, wound dehiscence, and delayed wound healing. In addition, the longer plate may cause more irritation to the surrounding soft tissues, including muscles, tendons, and nerves.
Conversely, a shorter DCP means a smaller incision and less soft - tissue damage. This can result in a quicker recovery time and fewer postoperative complications. However, as mentioned earlier, the need for stability must be balanced against the soft - tissue concerns. In some cases, a longer DCP may be necessary despite the potential soft - tissue issues to ensure proper fracture healing.
Clinical Evidence
Clinical studies have provided some insights into the relationship between DCP length and treatment outcomes. A meta - analysis of several clinical trials found that in humeral shaft fractures, patients treated with a longer DCP had a lower rate of non - union compared to those treated with a shorter DCP [3]. However, these patients also had a slightly higher incidence of postoperative complications related to soft - tissue problems.
In another study on femoral fractures, the use of a long DCP was associated with better alignment and fewer secondary procedures for fixation failure. But the long - term follow - up showed that some patients experienced bone atrophy near the plate, which was attributed to stress shielding [4].
Our Product Offerings
As a supplier of Dynamic Compression Plate, we understand the importance of providing a range of plate lengths to meet the diverse needs of orthopedic surgeons and patients. Our DCPs are available in various lengths, allowing for customized treatment based on the specific fracture characteristics.
In addition to the standard DCPs, we also offer specialized plates such as the Clavicle Hook Reconstruction Plate and the Calcaneus Plate. These plates are designed for specific fracture locations and have been engineered to provide optimal stability and promote healing.
Conclusion
The length of the Dynamic Compression Plate is a crucial factor that can significantly affect the treatment outcome of fractures. While a longer plate can provide better stability and stress distribution in many cases, it also comes with the risk of stress shielding and increased soft - tissue complications. On the other hand, a shorter plate may reduce soft - tissue damage but may not be sufficient for complex fractures.
Orthopedic surgeons need to carefully consider the fracture type, location, and the patient's overall condition when selecting the appropriate DCP length. As a supplier, we are committed to providing high - quality DCPs in a variety of lengths to support optimal treatment outcomes. If you are an orthopedic surgeon or a medical institution interested in our products, we invite you to contact us for further discussion and procurement. We are ready to work with you to provide the best solutions for fracture treatment.
References
[1] Müller ME, Allgöwer M, Schneider R, Willenegger H. Manual of Internal Fixation: Techniques Recommended by the AO Group. 3rd ed. New York: Springer - Verlag; 1991.
[2] Perren SM. The concept of biological plating: Fracture treatment without endangering the blood supply. Injury. 2002;33 Suppl 4: S15 - S26.
[3] Chen X, Zhang Y, Wang X, et al. Meta - analysis of the effect of plate length on the treatment of humeral shaft fractures. J Orthop Trauma. 2015;29(10): 563 - 568.
[4] Zlowodzki M, Bhandari M, Tornetta P 3rd, et al. Does the length of the plate influence the outcome of femoral shaft fractures treated with plate fixation? A systematic review. J Orthop Trauma. 2006;20(10): 701 - 707.