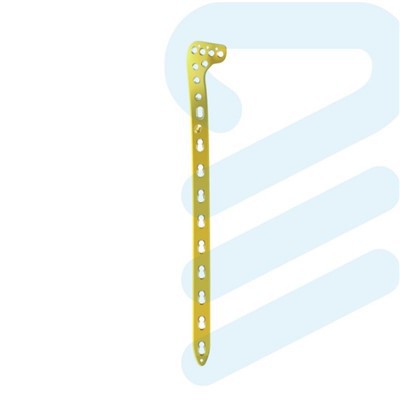
The learning curve represents the relationship between the proficiency of a task and the experience gained over time. In the context of surgical procedures, understanding the learning curve is crucial for both surgeons and patients. It helps predict the time and cases required for a surgeon to achieve a certain level of competence and consistency in performing a particular operation. For surgeons performing Clavicle Locking Plate surgery, a clear understanding of the learning curve can guide training programs, set realistic expectations for outcomes, and ultimately improve patient safety and surgical results.
Clavicle fractures are common injuries, accounting for about 2.6% of all fractures and 44 - 66% of shoulder girdle fractures. Clavicle Locking Plate surgery has become a popular treatment option due to its ability to provide stable fixation, allowing for early mobilization and better functional outcomes compared to non - operative management. However, like any surgical procedure, it comes with a learning curve.
Factors Affecting the Learning Curve
Surgical Complexity
The clavicle has a unique S - shaped anatomy, and its location in close proximity to important neurovascular structures such as the brachial plexus and subclavian vessels adds to the complexity of the surgery. Surgeons need to be extremely careful during dissection and plate placement to avoid damage to these vital structures. Additionally, the fixation of the clavicle locking plate requires precise reduction of the fracture fragments and accurate screw placement. Any misalignment or improper screw insertion can lead to poor fixation, non - union, or other complications.
Surgeon's Experience
Surgeons with prior experience in orthopedic trauma surgery may have a shorter learning curve for Clavicle Locking Plate surgery. Their familiarity with surgical techniques, anatomical knowledge, and experience in handling similar fractures can give them an advantage. For example, a surgeon who has performed multiple open reduction and internal fixation (ORIF) procedures on long bones may find it easier to adapt to the specific requirements of clavicle surgery. On the other hand, novice surgeons may take longer to become proficient as they are still developing their basic surgical skills and anatomical understanding.
Training and Mentorship
A well - structured training program and mentorship can significantly impact the learning curve. Surgeons who receive comprehensive training in clavicle anatomy, fracture classification, and surgical techniques are more likely to progress faster. Mentorship from experienced surgeons allows trainees to observe real - time surgeries, ask questions, and receive feedback on their performance. This hands - on learning experience can help them avoid common mistakes and accelerate their learning process.
Measuring the Learning Curve
Surgical Outcomes
One of the most common ways to measure the learning curve is by evaluating surgical outcomes. This includes factors such as fracture union rate, complication rate, and patient - reported outcomes. In the early stages of a surgeon's learning curve, the complication rate may be higher, and the fracture union time may be longer. As the surgeon gains more experience, these outcomes are expected to improve. For example, a study might track the rate of non - union, infection, and hardware failure in the first 10, 20, and 30 cases performed by a surgeon and compare them to established benchmarks.
Surgical Time
Surgical time is another important metric. In the beginning, surgeons may take longer to complete the Clavicle Locking Plate surgery as they are still getting familiar with the procedure. As they gain more experience, they become more efficient in performing each step of the surgery, leading to a reduction in surgical time. A significant decrease in surgical time over a series of cases can indicate that the surgeon is progressing along the learning curve.
Stages of the Learning Curve
Novice Stage
At the novice stage, surgeons are just starting to perform Clavicle Locking Plate surgery. They may be overly cautious, which can result in longer surgical times. The risk of complications is relatively high as they are still learning to handle the unique challenges of the procedure. For example, they may have difficulty in achieving proper fracture reduction or may be more prone to accidental damage to surrounding tissues.
Intermediate Stage
As surgeons gain more experience, they enter the intermediate stage. They start to become more comfortable with the surgical steps, and surgical time begins to decrease. The complication rate also starts to decline as they become more proficient in fracture reduction and plate fixation. However, they may still encounter occasional difficulties, especially in complex fracture patterns.
Expert Stage
In the expert stage, surgeons have achieved a high level of proficiency. They can perform the surgery efficiently, with a low complication rate and high fracture union rate. They are able to handle even the most complex clavicle fractures with confidence and precision.
As a Clavicle Locking Plate supplier, we understand the importance of the learning curve for surgeons. Our products, such as the Titanium Humerus Plate, Anatomical Locking Plate, and Titanium Locking Plate, are designed to meet the high - quality standards required for successful clavicle surgeries. Our plates are made from high - grade titanium, which offers excellent biocompatibility and mechanical properties, ensuring stable fixation and promoting bone healing.
We are committed to supporting surgeons in their learning process. We provide comprehensive product information, including detailed surgical guides and training materials. Our technical support team is also available to answer any questions and provide assistance during the surgical procedure.
If you are interested in learning more about our Clavicle Locking Plates or other orthopedic implants, we encourage you to reach out to us for a procurement discussion. We believe that by working together, we can improve the quality of clavicle surgeries and ultimately enhance patient outcomes.


References
- Robinson CM. Fractures of the clavicle in the adult. Epidemiology and classification. J Bone Joint Surg Br. 2002;84(5):547 - 554.
- Zlowodzki M, Cole PA, McKee MD, et al. Operative treatment of displaced midshaft clavicular fractures: a meta - analysis of randomized clinical trials. J Bone Joint Surg Am. 2007;89(1):1 - 10.
- Koval KJ, Zuckerman JD. Orthopaedic Knowledge Update: Trauma 4. Rosemont, IL: American Academy of Orthopaedic Surgeons; 2009.